English

English, Uncategorized

Teletherapy in 2026: Our Clinical Take on What AI Is Actually Changing

As therapists working daily in teletherapy, we have all felt the shift. AI is no longer something happening “out there” in tech headlines it is quietly entering our platforms, our workflows, and our clinical decision-making spaces. The question for us has never been whether AI will be used in therapy, but how it can be used without compromising ethics, clinical judgment, or the therapeutic relationship. Over the past year, we have actively explored, tested, and critically evaluated several AI-driven tools in teletherapy contexts. What stands out most is this: the most useful AI tools are not the loudest ones. They are the ones that reduce friction, cognitive load, and therapist burnout while preserving our role as the clinical authority. Expanding Access Without Diluting Care One of the most meaningful developments we’ve seen recently is how AI is being used to expand access to therapy rather than replace it. Platforms such as Constant Therapy have expanded their AI-driven speech and cognitive therapy programs into additional languages, including Spanish and Indian English. This matters clinically. It allows us to assign culturally and linguistically relevant home practice that aligns with what we are targeting in sessions, instead of relying on generic or mismatched materials. From our experience, this kind of AI-supported practice increases carryover without increasing preparation time something teletherapy clinicians deeply need. Conversational AI That Supports Continuity, Not Dependency Mental health platforms like Wysa, particularly with the introduction of Wysa Copilot, reflect a growing shift toward hybrid models where AI supports therapists rather than attempts to replace them. These systems help structure between-session support, guide reflective exercises, and support homework completion, all while keeping the clinician in the loop. When we tested similar conversational AI tools, what we valued most was not the chatbot itself, but the continuity. Clients arrived to sessions more regulated, more reflective, and more ready to engage because the therapeutic thread had not been completely paused between sessions. Speech and Language AI: Practice, Not Diagnosis Advances in automatic speech recognition have significantly improved the quality of AI-assisted speech practice tools. In articulation and fluency work, we’ve used AI-supported practice platforms to increase repetition, consistency, and feedback during teletherapy homework. Clinically, we see these tools as structured practice partners not assessors and certainly not diagnosticians. They help us gather cleaner data and observe patterns, but interpretation remains firmly in our hands. When used this way, AI becomes an efficiency tool rather than a clinical shortcut. Voice Biomarkers as Clinical Signals, Not Labels Another emerging area is the use of voice biomarkers tools that analyze vocal features to flag possible emotional or mental health risk markers. Tools like Kintsugi and Ellipsis Health are increasingly discussed in clinical AI spaces. When we explored these tools, we found them useful as conversation starters, not conclusions. In teletherapy, where subtle nonverbal cues can be harder to read, having an additional signal can help us ask better questions earlier in the session. We are very clear, however: these tools support clinical curiosity; they do not replace clinical judgment. Ethics, Regulation, and Our Responsibility Not all AI adoption has been smooth and rightly so. In 2025, several regions introduced restrictions on AI use in psychotherapeutic decision-making. From our perspective, this is not a step backward. It reflects a necessary pause to protect clients, clarify consent, and reinforce professional boundaries. As therapists, we carry responsibility not just for outcomes, but for process. Any AI tool we use must be transparent, ethically integrated, and clearly secondary to human clinical reasoning. What We’re Taking Forward Into Our Telepractice Based on what we’ve tested and observed, these are the principles guiding our use of AI in teletherapy: We use AI to reduce administrative and cognitive load, not to replace thinking.We choose tools grounded in clinical logic, not generic productivity hype.We prioritize transparency with families and clients about how technology is used.We treat AI outputs as data points, never as decisions. What feels different about teletherapy in 2026 is not the presence of AI it’s the maturity of how we engage with it. When AI is positioned as a background support rather than a clinical authority, it allows us to show up more present, more regulated, and more attuned to our clients. Teletherapy does not need less humanity. It needs protection of it. Used responsibly, AI helps us do exactly that.

English, Uncategorized

Wrapping Up 2025 A Year of AI in Therapy What We Learned and What We Expect Next

As we reach the end of the year, many of us are reflecting not just on our caseloads or outcomes, but on how much our daily practice has shifted. 2025 was not the year AI took over therapy. Instead, it was the year AI quietly settled into our workflows and pushed us as clinicians to become more intentional about protecting clinical judgment while embracing useful innovation. From speech therapy and mental health to teletherapy platforms, AI moved from experimental to practical. What matters now is how we, as therapists, choose to use it. AI This Year From Hype to Real Clinical Use One of the most noticeable changes in 2025 is how AI tools are being designed around clinicians rather than instead of them. Platforms such as Wysa, particularly through clinician supported tools like Wysa Copilot, reflect this shift. These systems are no longer simple chatbots. They now function as structured supports that help maintain therapeutic continuity between sessions while keeping clinicians in control. From our own testing and use, the value has not been in AI talking to clients, but in how it supports reflection, homework follow through, and emotional regulation between sessions. Clients arrive more prepared, and sessions feel less like a restart and more like a continuation. Speech and Language Practice Where AI Truly Helps In speech and language therapy, AI had its strongest impact this year in practice intensity and consistency. AI assisted articulation and voice practice tools now offer more accurate feedback and structured repetition that is difficult to achieve consistently between teletherapy sessions. We have used these tools as practice partners rather than assessors. They help us collect clearer data and observe patterns over time, while interpretation remains human. Their strength lies in freeing our cognitive space so we can focus on planning, adapting, and responding within sessions. Accessibility and Reach A Quiet Win Another important development this year has been the expansion of AI driven therapy platforms into additional languages and regions. Tools like Constant Therapy expanding into multiple languages signal something important. AI can reduce access barriers without lowering clinical standards. For teletherapy, this has translated into better carryover, more culturally relevant practice materials, and stronger engagement outside live sessions. Voice Based AI and Emotional Signals Used With Caution 2025 also brought increased attention to voice based AI tools that analyze speech patterns for emotional or mental health signals. Tools such as Kintsugi and Ellipsis Health are often mentioned in this context. From our experience, these tools work best as signals rather than answers. In teletherapy, where subtle cues can be harder to detect, they can guide deeper clinical questioning. They do not diagnose, and they should never replace observation, clinical interviews, or professional judgment. Ethics and Regulation Took Center Stage This year also reminded us that innovation without boundaries is risky. Increased regulation around AI use in therapy particularly related to crisis detection, consent, and transparency has been a necessary step. As clinicians, this aligns with what we already practice. Therapeutic work requires accountability, clarity, and human responsibility. AI must remain secondary to the therapeutic relationship. How We Are Using AI Going Forward As we close the year, these principles guide our clinical use of AI. We use AI to reduce administrative and cognitive load rather than replace thinking.We choose tools grounded in clinical logic and therapeutic models.We remain transparent with clients and families about AI use.We treat AI outputs as supportive data rather than clinical decisions. When used this way, AI becomes an ally rather than a distraction. Looking Ahead If 2025 was the year of testing and learning, the year ahead will likely focus on refinement. We expect clearer standards, better clinician informed design, and deeper conversations around ethics, inclusion, and sustainability. Most importantly, we expect the focus to return again and again to what matters most. Human connection, clinical reasoning, and ethical care. AI will continue to evolve. Our role as therapists remains unchanged. We interpret. We adapt. We connect.

English, Uncategorized

Zoom AI and Humanity’s Last Exam: Why This Matters for Therapists

Recently, Zoom announced that its AI system scored 48.1% on a benchmark called Humanity’s Last Exam, or HLE. At first, that number might not seem impressive. On a typical test, it would be a failing grade. But what makes this milestone interesting is what the exam actually measures and how Zoom’s AI achieved it. HLE was designed to test reasoning rather than memorisation. Most AI benchmarks measure pattern recognition. If a model has seen enough examples, it can often produce a correct answer without really understanding. HLE removes that safety net. Its questions cover a broad academic spectrum, from medicine and law to literature and philosophy. They are unfamiliar on purpose, requiring multi-step reasoning, problem-solving, and justification. A model must interpret a scenario, weigh possible explanations, and defend a final conclusion. It is not enough to recall information. The exam rewards logical thinking. What we found particularly interesting is how Zoom approached the problem. Instead of relying on one massive AI, they used multiple smaller models working together. Each model explores the problem from its own perspective, verifies the reasoning, and contributes to a final answer. Zoom calls this approach Explore, Verify, Federate. It mirrors the way we often work in clinical settings. When complex decisions arise, we collaborate with other specialists, weigh evidence, and integrate insights to reach the best conclusion. Smaller models focusing on what they do best can produce stronger reasoning than a single, oversized system. So why should therapists care about this? While AI is still far from human-level reasoning, this breakthrough hints at tools that could support clinical work in meaningful ways. We can imagine AI helping us analyse case notes and track patterns over time. It could suggest potential therapy activities, generate personalised visual or interactive tools, or provide structured summaries during teletherapy sessions. These systems could reduce repetitive tasks and free us to focus on the human connection that drives therapy outcomes. The federated approach also suggests AI could become more efficient and transparent. Instead of massive, opaque models, we could see networks of smaller reasoning engines that explain how they arrive at conclusions. For us, that means more trust in AI’s suggestions and better integration into multidisciplinary teams. HLE is not a signal that AI can replace therapists. It is a step toward reasoning-focused tools that work with us. By testing AI in challenging, unfamiliar scenarios, researchers are showing that the technology can begin to reason rather than just produce fluent text. For therapists, especially in teletherapy, this opens doors to smarter support systems, more personalised client engagement, and tools that help us plan, track, and refine interventions efficiently. We are still early in this journey, but milestones like Humanity’s Last Exam give us a glimpse into a future where AI can truly enhance our clinical practice. It won’t replace our judgment, but it can become a powerful partner in delivering thoughtful, data-informed, and engaging therapy

English, Uncategorized

AI Group Chats: A New Dimension of Clinical Collaboration

AI is evolving at a pace that is beginning to reshape how therapists plan, create, and communicate. The newest feature to emerge from OpenAI—group chats within ChatGPT—opens a door to something far broader than individual support. It invites us into a shared thinking space, where professionals can co-create, exchange knowledge, and build clinical ideas together in real time. The concept is simple: instead of interacting with ChatGPT alone, up to twenty people can now join a single conversation. Each participant can add content, ask questions, bring examples from their field, or collaborate on documents while the AI remains available as a full conversation member. This creates a shared cognitive environment where ideas can move faster and develop in richer directions. From a therapy and rehabilitation perspective, this feels significant. Many of us work inside multidisciplinary teams. We collaborate with occupational therapists, psychologists, physical therapists, special educators, literacy specialists, and colleagues across languages and disciplines. Much of that collaboration happens through email threads, delayed messages, and informal discussions squeezed between appointments. The new group environment allows that entire process to become more fluid and immediate. When tested in clinical, content-building, and planning scenarios, it revealed an interesting strength. The AI is not simply answering questions. It behaves like a supportive peer who can step back, observe, and intervene only when needed. In interdisciplinary content creation, this becomes particularly powerful. Imagine a group of professionals drafting therapy materials together. Speech therapists contribute language goals, OTs focus on sensory integration or motor sequencing, psychologists add emotional framing, and educators ensure academic alignment. Instead of sending documents back and forth, you can see the draft evolve live, with the AI suggesting formulations, rephrasing language to be child-friendly, comparing two versions of an activity, or helping structure visual supports. In planning interdisciplinary sessions, the group chat can support goal alignment. You can outline each objective, ask the AI to check overlap or redundancy, and generate a structured session design in minutes. For therapists who constantly balance workload with documentation demands, this creates a major time advantage. Creative brainstorming also becomes more dynamic. When producing visuals, prompts, narrative story frames, or creative play ideas, the presence of several minds and a responsive AI provides diversity of thought that is difficult to replicate alone. All that said, the technology brings more than excitement. It brings responsibility.The strongest benefit appears when clinicians enter the space with intentionality. AI should not guide clinical decisions; it should support infrastructure, wording, creativity, and clarity. It cannot replace judgment, assessment skill, or reasoning. What it can do is amplify them. Privacy naturally remains a key focus. OpenAI’s structure places group decision-making and consent at the front of the design. Group chats are optional and separate from personal chats. Memory from private conversations does not carry into the shared environment, and the AI does not merge histories between users. However, that does not replace our ethical obligations. Patient-identifiable information should never be included. Notes, reports, names, or confidential data must remain protected within secure clinical systems. What emerges is a model of collaboration we have not experienced before. Instead of isolated conversations with the AI, we now have a genuine shared panel where professionals can think together. The result blends human insight with technical support in a way that potentially transforms workflow. Some early applications in therapy and rehabilitation may include: • Interdisciplinary brainstorming sessions for complex cases using de-identified clinical themes.• Co-writing therapy manuals, parent handouts, home programs, and lesson plans.• Developing school-based or clinic-based intervention frameworks that integrate multiple viewpoints.• Group training sessions for students or interns learning clinical reasoning. The value does not lie in AI producing answers for us. It lies in the structure it offers. Consistency, clarity, and streamlined collaboration are not small achievements in a field where time and cognitive load are serious challenges. For therapists working in modern healthcare environments, this may signal a shift. We are moving from individual AI interaction toward collective AI-supported teamwork. And that change appears to be arriving faster than expected. AI will not decide how you treat a patient. It will not evaluate speech samples for you or diagnose a disorder. But it can help you outline a treatment pathway, compare therapy approaches, or turn fragmented ideas into polished, shareable documents. Used wisely, group chats become a thinking enhancer rather than a thinking replacement. This development is not a promise of what might happen in five years. It is available now, and early users are already exploring its potential. As therapists, we can decide how deeply we want to engage, how responsibly we want to shape this tool, and how creatively we want to use the new collaborative space it provides.

English

AI-Assisted Data Tracking for Therapy: How Google Tools Can Improve Progress Monitoring

If you’re like us, you know how important tracking progress is in therapy. But let’s be honest—it’s also one of the most time-consuming parts of the job. We’ve all spent more hours documenting than actually connecting with clients, and that’s just not sustainable. That’s why we decided to give Google’s AI tools a try, and here’s what we discovered. We started using Google Sheets with its new AI features to streamline our data tracking. Instead of manually entering formulas or calculating accuracy rates, we just asked Sheets to “summarize the trend of correct responses for the last 8 sessions” or “highlight any sessions where accuracy dropped more than 10%.” It’s surprisingly intuitive, even if you’re not a spreadsheet expert. The best part? It frees up so much time—time we can spend interpreting the data, not just crunching it. For example, we used to spend 15–20 minutes per client session just organizing data, but now we’re down to 5–7 minutes, which adds up over a busy week. Automating repetitive calculations—like percent accuracy, frequency counts, and error patterns—is a lifesaver, especially when juggling multiple clients or managing large caseloads. We also love how easy it is to generate visual charts. For example, we can request a line chart showing progress on a specific goal, and Sheets creates a clear, shareable visual. Families and multidisciplinary teams find these charts really helpful, and it’s a great way to show clients their progress in a tangible way. One parent told us, “Seeing the chart made it easier to understand my child’s progress, and it gave us hope when things felt slow.” Another win: Google’s AI can take our raw session notes—just bullet points or keywords—and turn them into clear, objective summaries. It’s not perfect, but it’s a huge time-saver, especially after back-to-back sessions. Plus, the AI can scan multiple sessions to spot patterns we might miss, like recurring errors or triggers for certain behaviors. While we still interpret what those patterns mean, the AI speeds up the process and helps us catch details we’d otherwise overlook. For instance, we noticed that a child’s language gains were stronger on days with more structured routines, which led us to adjust our intervention plan. There are some hiccups, though. The AI doesn’t always get the nuance right, so we still need to review and tweak the summaries and charts. Also, there’s a learning curve—some therapists might feel overwhelmed at first, especially if they’re not tech-savvy. And of course, privacy is a big concern. We always double-check that our data is stored securely and that we’re following all the necessary guidelines, especially when working with minors. We use Google’s built-in privacy controls and make sure our clients’ information is never shared without consent. But here’s where it gets tricky: how is your patient data stored? Where is it stored? How is it used to train models or used internally? What can you actually do as a therapist to protect client confidentiality? Where are these files kept, and what controls do you have over access and sharing? These are all critical questions we’re still exploring, and it’s important to stay informed about Google’s privacy and security policies. If you want to know more, join our upcoming training sessions or reach out to us—there’s a lot to unpack, and we’re here to help you navigate it all. Overall, Google’s AI tools have made our data tracking smarter and more efficient. They don’t replace the human touch—clinical judgment, empathy, and context are still irreplaceable—but they do help us focus more on what matters: building connections with clients, practicing skills, and responding to their unique needs. If you’re looking to spend less time on admin and more time on therapy, it’s definitely worth giving these tools a try. AI is not here to replace us; it’s here to help us do our jobs better. When used thoughtfully, these tools can amplify our ability to track progress accurately and support families with the insights they deserve. So go ahead—give AI-assisted data tracking a shot. You might just find it as helpful as we did.

English

Inside Google’s AI Ecosystem: How Gemini, AI Studio, and Agents Are Quietly Transforming Therapy and Education

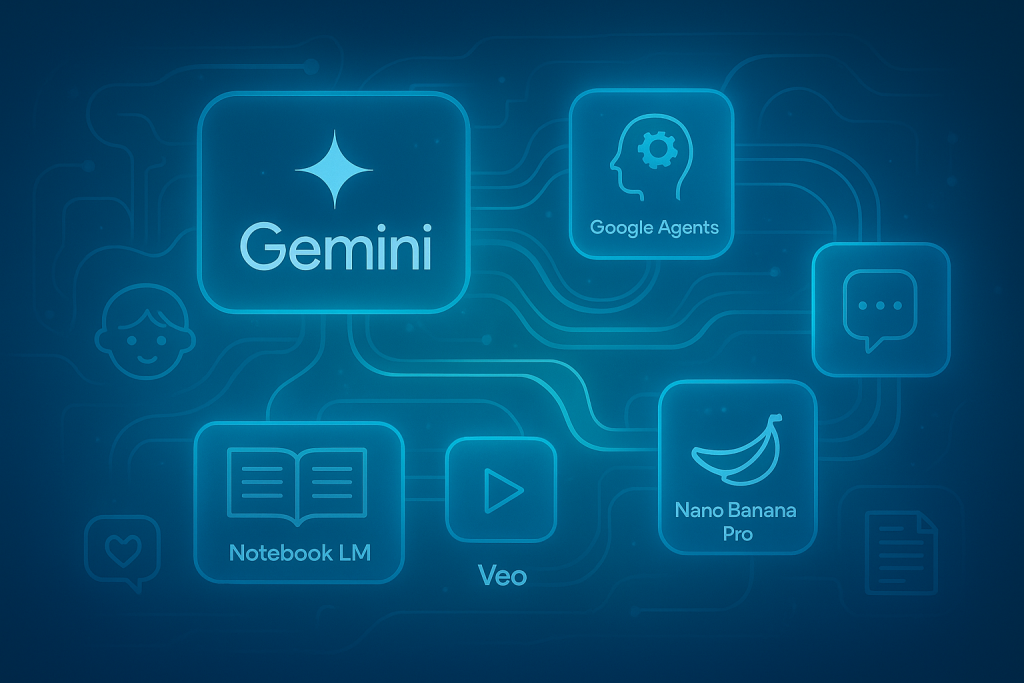
Over the past year, we’ve been diving into Google’s AI ecosystem, and honestly, it’s been a game changer for how we work in therapy and education. It’s not just about Gemini anymore—it’s about how all these tools, from AI Studio to agents, Notebook LM, and a whole range of other apps, fit together to create a workflow that feels like it’s actually built for busy clinicians and educators. We started with Gemini, Google’s multimodal AI, and quickly realized how much it could help with generating structured, clinically relevant content. Whether it was creating a social story tailored to a child’s sensory profile or simplifying a linguistic concept for a parent, Gemini’s strength is its ability to understand detailed prompts and deliver useful drafts. What we liked most was that, with clear context, Gemini could produce materials that felt personalized and relevant, saving us hours of prep time. But we also noticed its limitations—it’s not a replacement for clinical expertise, and sometimes it needed a lot of tweaking to get the nuance right. Then we explored Google AI Studio, which lets you build custom tools that reflect your own style or caseload needs. We created a simple “social story generator with sensory-friendly wording” and a “WH-question practice tool for early language learners.” The best part? You don’t need to be a coder—building something useful is surprisingly approachable. When you automate one repetitive task, like generating session summaries or parent guidance emails, it compounds over time. We’ve saved hours each month just by having these tools ready to go. At the top layer, Google’s agent technology is starting to handle more complex, multi-step workflows. Agents can read your weekly goals, categorize them by child, draft session plans, update progress-tracking documents, and even prepare parent emails. At first, the idea of fully automated workflows felt a bit intimidating, but we’ve found that even partial automation—like auto-generating weekly reports or sorting client data—can reduce cognitive fatigue and free up mental space for the human side of our work. The key is to keep control: agents are assistants, not replacements. We also tested out Google Notebook LM, which lets you upload your own documents and have the AI summarize, analyze, or even draft responses based on your notes. For therapy planning and research, it’s been a helpful way to organize and extract insights from our own files. And with Google’s AI-powered features in Sheets and Docs, automating calculations and generating visual charts has become seamless. Other apps like Google’s AI-powered Chromebooks, with their advanced text-to-speech and dictation, have also made a difference, especially for learners who need accessibility support. Google Meet’s real-time transcription and translation has been a game changer for sessions with non-native speakers or when we need to share clear summaries with parents. Google Forms with AI-powered smart surveys has made collecting feedback and tracking progress even easier, and Google Slides with AI design suggestions helps us create visually engaging presentations for training or parent workshops. But the real excitement for us has come from experimenting with Nano Banana and Nano Banana Pro. Nano Banana is a quick AI content generator that makes it easy to create engaging educational graphics, course visuals, and teaching materials on the fly. It’s especially useful for making complex concepts accessible and memorable. Nano Banana Pro takes it up a notch, offering high-quality, emotionally expressive video and image generation. It’s a game-changer for personalized intervention videos, social stories, and step-by-step demonstrations—making it easier than ever to model skills, routines, or emotional scenarios for our clients and students. Veo, Google’s video generation tool, is another standout. It lets us create custom videos for therapy explanations, lessons, or visual supports in minutes. Whether it’s a short video to demonstrate a skill, explain a concept, or engage a student, Veo streamlines production and saves valuable time. Don’t forget about Google’s AI-powered search, which now surfaces research and resources tailored to our specific needs, and Google Keep with AI-powered reminders and notes organization, which keeps our to-do lists and session notes in order. And for those who love experimenting, Google’s new AI-powered “Studio” features in Docs and Slides let you generate images, charts, and even entire slide decks with just a few clicks. What we appreciate most is how all these tools are designed to work together. You can start with a prompt in Gemini, build a custom tool in AI Studio, use agents for workflow automation, analyze your results in Notebook LM, and then share your findings with Meet, Slides, or Keep—all within Google’s ecosystem. The integration is smooth, and it feels like these tools are actually built to support the way we work, not just add another layer of complexity. Of course, there are downsides. Privacy is always a concern, and we make sure to never upload client-identifying information. And while these tools are powerful, they still need human oversight—no AI can replace clinical judgment or the therapeutic relationship. But when used thoughtfully, Google’s AI ecosystem can significantly boost efficiency, personalize materials, and reduce the administrative load that often takes up so much of our time. Look out for future editions of the Happy Brain Training newsletter for more information, tips, and updates on how these tools are evolving and how you can use them safely and effectively in your practice.

English

The Mind-Reading AI? How Brain-Computer Interfaces Are Changing Therapy Forever

What if artificial intelligence could read your thoughts — not to spy on you, but to heal your brain? It may sound like science fiction, yet emerging research in brain-computer interfaces (BCIs) powered by AI is rapidly reshaping possibilities for people with paralysis, speech loss, or severe trauma. For professionals working in therapy, special education, and neuroscience, this isn’t just a technologic novelty — it signals a fundamental change in how we might approach intervention, autonomy, and recovery. Decoding the Brain: How BCIs and AI Work At their core, BCIs translate neural activity into digital commands. Historically, these devices captured signals (via EEG, implanted electrodes or minimally-invasive sensors) that corresponded with a user’s intention — like moving a cursor or selecting a letter. The leap now comes from AI. Sophisticated machine-learning and deep-neural-network models can decode nuanced brain patterns, adjust in real time, and even predict states such as mood shifts or seizure events. For example, a man with partial paralysis used a non-invasive BCI-AI hybrid system to control a robotic arm and complete screen-based tasks four times more effectively than with the device alone. This is not automation—it’s collaboration. The AI decodes the signal, but the human leads the intention. As a practitioner, it means thinking of BCIs not as “devices we deliver to clients” but as extensions of the therapeutic interface — neural input, meaningful output, and a feedback loop that connects brain to device, device to action, and action to meaning. Breakthroughs in 2024-25: From Paralysis to Restoration Recent stories illustrate the pace of change. A 2025 article reported how a man with paralysis controlled a robotic arm via thought alone, thanks to an AI-enhanced BCI. Another major milestone: the company Medtronic’s BrainSense Adaptive Deep Brain Stimulation system — a closed-loop BCI-informed therapy for Parkinson’s — was named one of TIME’s “Best Inventions of 2025” after more than 1,000 patients received the treatment. These examples aren’t just about technology; they’re about therapy delivered at the brain level. Speech therapists, neurorehabilitation professionals, and educators who support motor recovery might soon interact with clients whose therapy includes neural-interface elements: devices that decode intention, guide movement, or translate thought into speech. For many clients, the promise of regained autonomy—typing messages, controlling assistive devices, or even walking—becomes real. Ethical and Practical Considerations for Clinical Practice Despite the excitement, the shift from novelty to mainstream carries enormous responsibility. Data from neural interfaces is intensely personal: thinking, intending, perhaps even emoting. Decoding inner speech raises privacy questions. One recent implant study could interpret a user’s “inner monologue” with up to 74% accuracy. As clinicians or educators, we must ask: how do we preserve dignity, agency, and consent when the very channel of thought becomes part of therapy? Accessibility is another concern. These technologies are highly specialist, invasive in certain cases, and expensive. Without careful integration, we risk creating a two-tier system where only some clients benefit. The research commentary on BCIs in 2025 notes that despite dramatic advances, many devices still require frequent recalibration and remain confined to labs. From a practice standpoint, we’re entering the era of hybrid therapy—one where neural devices, AI analytics, and human relational expertise converge. Our role expands: we’re interpreters of neural data, ethical stewards of device use, and guides of clients whose therapy includes machine-mediated experience. The therapeutic alliance doesn’t disappear—it deepens. For therapists, special educators and researchers, the rise of AI-enabled BCIs signals three shifts: In effect, the future of rehabilitation and intervention may involve thought, device, and context in tandem—with the human at the centre, but AI and BCIs as powerful allies. While fully mainstream neurotechnology may still be a few years away, the trajectory is clear. We might soon design therapy plans that include neural intention measurement, adaptive devices that respond to brain-states, and home-based neural support systems. For now, staying informed, curious and ethically grounded is vital. When the channel of change is the brain itself, our practice must become correspondingly profound. Suggested Reading: Live Science (2025): The new implant that can decode inner speech

English

AI Ethics in Healthcare — Building Trust in the Age of Intelligent Therapy

Artificial intelligence has woven itself into the fabric of modern healthcare. From diagnostic imaging to speech and language therapy, AI now touches nearly every aspect of practice. But as the technology grows more powerful, so does the need for clear ethical boundaries. Recent international reports and consensus statements show that 2025 may be remembered as the year the world finally agreed on what “ethical AI in healthcare” must look like. Across countries and disciplines, regulators and researchers are converging on similar principles: transparency, accountability, fairness, and above all, human oversight. The International Medical Committee of Research (ICMR) recently published its Ethical Guidelines for the Application of Artificial Intelligence in Biomedical Research and Healthcare, a comprehensive document outlining the responsibilities of professionals who use AI in health-related contexts. These guidelines call for explicit consent procedures, clear communication about the use of AI, and strong governance around data protection. At the same time, the World Medical Association (WMA) released its summary document on the Ethical, Legal, and Regulatory Aspects of AI in Healthcare — a blueprint that urges health and therapy professionals to safeguard autonomy and to ensure that the “human-in-the-loop” principle remains non-negotiable. This echoes the FUTURE-AI framework, published in The BMJ, which identifies seven pillars for trustworthy AI: fairness, transparency, human-centeredness, robustness, explainability, accountability, and sustainability. For therapists, educators, and clinical researchers, these frameworks are more than abstract policies — they are practical guardrails. As AI becomes more embedded in clinical systems, therapists may rely on algorithmic suggestions to guide interventions, predict outcomes, or tailor materials. Yet ethical AI demands that professionals remain critical thinkers, not passive users. A language model may suggest a therapy strategy or generate a progress note, but it cannot capture the emotional subtleties, ethical dilemmas, or contextual nuances that define human care. The implications for practice are profound. When integrating AI tools — whether a language analysis app, an adaptive learning system, or a mental health chatbot — professionals must consider how these tools handle data, what assumptions shape their algorithms, and whether clients fully understand the role of AI in their care. Informed consent becomes a living process, not a one-time checkbox. Ethical AI also requires vigilance against bias. Many datasets that train AI systems underrepresent neurodiverse populations, minority language users, or people from low-resource contexts. When bias is embedded in data, it is embedded in outcomes — potentially amplifying inequities rather than reducing them. The current international guidelines call on practitioners to advocate for inclusivity in AI design, urging collaboration between clinicians, technologists, and patient communities. Ultimately, the question is not whether AI should be part of healthcare — it already is — but how we ensure it serves humanity rather than undermines it. The future of therapy and rehabilitation will likely be hybrid: human judgment empowered by machine intelligence. But the ethical compass must always point toward empathy, consent, and equity. Professionals who engage early with these ethical frameworks position themselves as leaders in responsible innovation. Reading and reflecting on them isn’t just regulatory compliance — it’s professional integrity in action. Further Reading:

English

OpenAI’s 2028 Vision: The Rise of Fully Autonomous AI Researchers

The pace of artificial intelligence advancement has been staggering, but OpenAI’s latest announcement marks a turning point that could redefine scientific discovery itself. By 2028, the company aims to develop fully autonomous AI researchers—systems capable of independently conceiving, executing, and refining entire scientific studies without human intervention. This isn’t merely an evolution of existing tools; it represents a fundamental shift in how knowledge is generated, one that promises to accelerate breakthroughs in fields ranging from neuroscience to education while forcing us to confront profound questions about the nature of research, authorship, and human expertise. The implications for scientists, clinicians, and educators are immense. Imagine an AI that doesn’t just assist with data analysis but actively designs experiments based on gaps in current literature, adjusts methodologies in real-time as new evidence emerges, and publishes findings that push entire fields forward. For researchers drowning in the ever-expanding sea of academic papers, this could mean identifying meaningful patterns in days rather than years. Therapists might gain access to personalized intervention strategies derived from millions of case studies, while special educators could receive AI-generated instructional approaches tailored to individual learning profiles. Yet with these possibilities comes an urgent need to consider: How do we ensure these systems serve human needs rather than commercial interests? What happens when AI makes discoveries we can’t fully explain? And how do we maintain ethical standards when the researcher is an algorithm? OpenAI’s roadmap to this future unfolds in deliberate stages, with the first major milestone arriving in 2026. By then, the company expects to deploy AI systems functioning as research interns—tools sophisticated enough to synthesize existing literature, propose testable hypotheses, and even draft experimental protocols with minimal human oversight. This intermediate step is crucial, as it allows the scientific community to adapt to AI collaboration before full autonomy becomes reality. The transition will require more than just technological advancement; it demands a cultural shift in how we view research. Peer review processes may need to evolve to accommodate AI-generated studies. Funding agencies might prioritize projects that leverage these tools effectively. And perhaps most importantly, researchers themselves will need to develop new skills—not just in using AI, but in critically evaluating its outputs, understanding its limitations, and ensuring its applications align with ethical principles. The potential benefits are undeniable. In psychology, an autonomous AI researcher could analyze decades of therapy outcome data to identify which interventions work best for specific demographics, leading to more effective treatments. In special education, it might design and test personalized learning strategies for students with unique cognitive profiles, offering educators evidence-based approaches they previously lacked. Even in fundamental science, AI could accelerate the pace of discovery by running thousands of virtual experiments in the time it takes a human lab to complete one. Yet these advantages come with significant risks. Without careful oversight, AI systems could perpetuate biases present in existing data, overlook nuanced human factors that don’t fit neat statistical patterns, or even generate findings that appear valid but lack real-world applicability. The challenge, then, isn’t just building these systems—but building them responsibly. As we stand on the brink of this new era, the scientific community faces a critical choice. We can approach this transition reactively, waiting to address problems as they arise, or we can take a proactive stance, establishing guidelines, ethical frameworks, and validation processes now. The latter approach requires collaboration across disciplines—computer scientists working with ethicists, clinicians partnering with AI developers, and educators helping shape how these tools integrate into real-world practice. It also demands public engagement, as the implications extend far beyond academia. When AI begins making discoveries that affect healthcare, education, and policy, who decides how those findings are used? The answers to these questions will determine whether this technological leap empowers humanity or leaves us struggling to keep up with machines that outpace our understanding. Ultimately, the rise of autonomous AI researchers isn’t just about faster science—it’s about redefining what research means in an age where human and machine intelligence intertwine. The goal shouldn’t be to replace human researchers, but to create a synergy where AI handles the heavy lifting of data and computation while humans bring creativity, ethical judgment, and real-world insight. If we navigate this transition thoughtfully, we could unlock a new golden age of discovery—one where the most pressing questions in psychology, education, and medicine find answers at an unprecedented pace. But if we fail to prepare, we risk creating a system where the pursuit of knowledge outpaces our ability to use it wisely. The clock is ticking; 2028 is closer than it seems, and the time to shape this future is now.

English

The 2026 Milestone: AI Research Interns and the Changing Face of Scientific Collaboration

The scientific community stands at the threshold of a transformative shift. By September 2026, OpenAI plans to introduce AI systems capable of functioning as research interns—tools that go beyond simple data analysis to actively assist in literature synthesis, hypothesis generation, and experimental design. This development marks more than just a technological upgrade; it represents the first step toward a future where artificial intelligence becomes an integral partner in the research process. For psychologists, neuroscientists, and educators, this shift could mean faster insights, more efficient studies, and unprecedented opportunities for discovery—but it also demands a fundamental rethinking of how we conduct, validate, and apply scientific knowledge. The concept of an AI research intern might sound abstract, but its practical applications are both immediate and profound. Consider a clinical psychologist investigating new therapies for anxiety disorders. Today, the process begins with months of literature review, sifting through hundreds of studies to identify gaps and opportunities. An AI intern could accomplish this in hours, not only summarizing existing research but highlighting unexplored connections—perhaps noticing that certain demographic groups respond differently to mindfulness-based interventions, or that combination therapies show promise in understudied populations. From there, the AI might propose specific hypotheses (“Would adding a social skills component improve outcomes for adolescents with comorbid anxiety and autism?”) and even draft preliminary study designs, complete with sample size calculations and methodological considerations. For researchers accustomed to the slow, labor-intensive nature of academic work, this level of support could dramatically accelerate the pace of discovery, allowing them to focus on the creative and interpretive aspects of their work rather than the mechanical. Yet the introduction of AI interns isn’t just about efficiency—it’s about changing the very nature of research collaboration. Traditional scientific work relies on human intuition, serendipitous connections, and deep domain expertise, qualities that AI currently lacks. The most effective use of these tools will likely emerge from a hybrid approach, where AI handles the repetitive and data-intensive tasks while human researchers provide contextual understanding, ethical oversight, and creative problem-solving. For instance, an AI might identify a statistical correlation between early childhood screen time and later attention difficulties, but it would take a developmental psychologist to interpret whether this reflects causation, confounding variables, or cultural biases in the data. Similarly, in special education research, an AI could analyze vast datasets on reading interventions, but an experienced educator would need to determine how those findings apply to individual students with complex, multifaceted needs. The integration of AI interns also raises critical ethical and practical questions that the scientific community must address proactively. One of the most pressing concerns is validation. How do we ensure that AI-generated hypotheses are rigorous and reproducible rather than artifacts of flawed data or algorithmic bias? Peer review processes may need to adapt, incorporating AI literacy as a standard requirement for evaluators. Funding agencies might develop new criteria for AI-assisted research, ensuring that proposals leverage these tools responsibly. And journals will face the challenge of authorship and transparency—should AI systems be credited as contributors? If so, how do we distinguish between human-led and AI-driven insights? Another significant consideration is equity. While AI interns could democratize research by giving smaller labs and underfunded institutions access to powerful analytical tools, they could also exacerbate existing disparities if only well-resourced teams can afford the most advanced systems. OpenAI and similar organizations have a responsibility to prioritize accessibility, perhaps through open-source models or subsidized access for academic researchers. Similarly, there’s a risk that AI systems trained primarily on data from Western, educated, industrialized populations could overlook or misrepresent other groups, reinforcing biases in scientific literature. Addressing this requires diverse training datasets and inclusive development teams that understand the limitations of current AI models. Perhaps the most profound impact of AI research interns will be on the next generation of scientists. Graduate students and early-career researchers may find themselves in a radically different training environment, where traditional skills like manual literature reviews become less essential, while AI literacy, prompt engineering, and critical evaluation of machine-generated insights grow in importance. Academic programs will need to evolve, teaching students not just how to use AI tools, but how to think alongside them—when to trust their outputs, when to question them, and how to integrate them into a human-centered research process. This shift could also reshape mentorship, with senior researchers guiding juniors not just in experimental design, but in navigating the ethical and practical challenges of AI collaboration. As we approach the 2026 milestone, the scientific community would be wise to prepare rather than react. Researchers can begin by experimenting with current AI tools, such as literature synthesis platforms like Elicit or data analysis assistants like IBM Watson, to understand their strengths and limitations. Institutions should develop guidelines for AI-assisted research, addressing questions of authorship, validation, and bias mitigation. And perhaps most importantly, we must foster interdisciplinary dialogue, bringing together computer scientists, ethicists, domain experts, and policymakers to ensure that these tools are designed and deployed responsibly. The arrival of AI research interns isn’t just a technological advancement—it’s a cultural shift in how we pursue knowledge. If we embrace this change thoughtfully, it could liberate researchers from tedious tasks, accelerate meaningful discoveries, and open new frontiers in science. But if we fail to engage with its challenges, we risk creating a system where the speed of research outpaces its quality, where algorithmic biases go unchecked, and where human expertise is undervalued. The choice isn’t between rejecting AI or accepting it uncritically—it’s about shaping its role in a way that enhances, rather than diminishes, the pursuit of truth. The countdown to 2026 has begun; the time to prepare is now.

Shopping Cart